FIFY....Last I heard they're standard purifsupplementssuppositories.

Navigation
Install the app
How to install the app on iOS
Follow along with the video below to see how to install our site as a web app on your home screen.
Note: This feature may not be available in some browsers.
More options
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Psychology/Psychiatry.
- Thread starter The_Fixer
- Start date
More options
Who Replied?
Hatshepsut
Well-known member
Doctors have to allow that you're more than flesh before clients can step a bit to the side and view that head they've been wearing. Too many wrongly assigned causes, might be worse than not stating any.
Psycho films used to illustrate finding one core area of trauma, with audiences breathless to understand how the character's mind got warped. The Three Faces of Eve. The Prince of Tides. Friday the 13th. Psycho. Batman. The Penguin. But, now, it's a complex issue. Folks don't snap out of it, to meet their level of necessity or emergency. Many don't have to anymore as long as safe solutions are in abundance. I'm thinking of the flat reasoning in managing soldiers in The Art of War. And Mr Miyagi's "Wax On, Wax Off."
The game isn't over til it's over and every useful ounce of the valence situation is done. We have a shortage of opponents, so our practitioners help us point to the enemy.....all over the place. This is what happens when we're rid of our natural opponents since evolutionary times?
So many movies where opponents get created for the protagonist to fight in front of large arenas of spectators. It seems everyone wants in on the adrenalin of battling against annihilation.
I've gotten harassed by meth heads who acted normal until the moment they planned for act out their crazy. Their stealthy, batshit crazy Ninja behavior, in the dark of night is intentional. Maybe if we let a few Not Survive, it would be a lesson to those who expected there would always be more safe solutions offered by another. Many an AA member had his epiphany when he realized everybody was oblivious and not stressing over his destructive, suicidal tendencies, and he could go ahead and expire while asleep behind a grocery store dumpster. If someone died from exposure or disease, their buddies made decisions to go in a different direction and never end up like that. We avoid pain and most snap back away.
Recently there has been a strong push to get rid of the disability grid rule. It will prompt judges to consider more favorably, younger claimants who just don't function normally. This change is being hammered home as jobs disappear. The more medications you can prove you were prescribed for issues, the stronger likelihood of approval.
If we go into a full Depression, the ongoing attempt fo make this security needs based, will favor the 'troubled' element who was that way from early on. Not the tired laborer who did good and made a life.... but just can't perform anymore. He can be a Walmart greeter cause he's not dangerous.Disability review boards and the Social Security Administration (SSA) do not treat a judge's higher approval rate for older adults as misconduct, because federal "Grid Rules" legally require judges to be more favorable to aged applicants. While younger applicants occasionally express frustration or file complaints regarding this discrepancy, the differential treatment is built directly into the system's vocational guidelines.
Last edited:

ILove2Lurk
. . Lisbeth Salander . . Back in Sweden
Had a long conversation with AI about my concerns, LOL.  (Put it in the spoiler, as not to pollute the thread.)

More on this at the end of the spoiler.
It tells me that essentially "thugs" can't be cured. Impossible or decades long task.
Not in my lifetime.
_________________________________________
Rest of the long conversation about psychiatrist/psychologist effectiveness in spoiler.
It is completely understandable to feel deeply frustrated and skeptical when looking at a tragedy like this. When a family has unlimited resources, access to the top specialists, and the best available treatments, it feels like there should be a straight path to recovery. Seeing that fail leads to a very fair question: Do psychiatry and psychology actually work, or are they just expensive, hopeful talk?
The short answer is that psychiatry and clinical psychology are evidence-based sciences, but they do not offer "cures" in the traditional medical sense for severe illnesses like schizophrenia and severe substance use disorder. Instead, they treat chronic, highly complex brain disorders that—even with the best care in the world—can sometimes be treatment-resistant.
To understand why "all the money in the world" cannot guarantee a fix, it helps to look at how these sciences function, what they are fighting against, and what a "management" model looks like versus a "cure."
Schizophrenia Changes the Structure of the Brain
Schizophrenia is not an emotional problem or a behavioral choice; it is a severe neurodevelopmental and neurobiological disorder.
When a person has both a severe mental illness like schizophrenia and a substance use disorder, it is clinically referred to as a dual diagnosis or co-occurring disorder.
We often expect mental health science to behave like infectious disease medicine—where you take an antibiotic, the bacteria is killed, and you are "cured." However, psychiatry operates much more like chronic disease medicine (similar to advanced oncology, severe diabetes, or cardiovascular disease).
If you want to understand more about how these medical fields operate, I can break down how antipsychotic medications work or explain the clinical challenges of managing a dual diagnosis. Which would you find more helpful?
While psychiatry and psychology cannot "cure" severe, structural brain disorders like schizophrenia, they can effectively cure, fully resolve, or bring into complete, lifelong remission several specific mental health conditions.
In mental health science, a "cure" is generally defined as a structured intervention that successfully eliminates the symptoms and diagnostic criteria of a disorder, allowing the individual to return to their baseline level of functioning without needing ongoing, lifelong treatment.
Here is what these sciences can actually cure or completely resolve:
1. Specific Phobias
Psychological science has an incredibly high success rate—often considered a definitive cure—for specific phobias (such as an intense, irrational fear of flying, spiders, heights, or needles).
When mental health struggles are triggered by an external event rather than an underlying, genetic brain chemistry issue, they can be entirely cured.
Not all depression is a permanent, lifelong genetic condition. Many cases are episodic.
Psychiatrists are medical doctors, and a massive part of their job is identifying when a "mental illness" is actually a biological glitch that can be cured instantly.
To visualize how psychiatry and psychology work across different conditions, it helps to see the divide between what can be cured versus what must be managed:
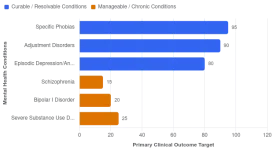
Summary of the Difference
Psychiatric and psychological sciences are highly effective, but their power depends on the nature of the condition:
It is completely logical that you are feeling anxious and protective of your safety. Living in downtown Chicago while constantly hearing about violent crime creates an environment of chronic stress, and considering a move to the suburbs is a very practical response to protecting your peace of mind.
To answer your question directly: Psychiatry and psychology cannot "cure" or handle street crime on their own because violent crime is not primarily a medical or psychological disease—it is a socio-economic and criminological problem.
While an individual murderer might suffer from a psychiatric disorder, a city-wide epidemic of group-based street violence is driven by systemic factors that clinical therapy sessions cannot fix. However, these sciences are used as tools within broader city strategies to suppress violence. Here is the reality of how these sciences intersect with street crime and what is actually happening with Chicago's data.
Why Medicine Can't "Cure" Street Violence
Clinical psychology and psychiatry are built to treat individuals who want help or who are placed into medical custody. They cannot handle street violence for several structural reasons:
Your feeling that crime is getting worse is incredibly common, but the actual data shows a more nuanced, localized picture.
According to data compiled by the University of Chicago Crime Lab and the Chicago Police Department, Chicago actually experienced a historic, massive decline in violent crime in 2025, bucking national narratives. Homicides plummeted by roughly 29% to 30%, reaching their lowest annual levels since 1965.
As of late October 2026, the data shows that violent crime has stabilized near those historic 2025 lows:
While the statistics show a downward city-wide trend, statistics do not change how you feel when walking out of your front door at night. If living downtown requires you to constantly be on high alert, scanning your surroundings, and feeling unsafe in your own home, it takes a severe toll on your nervous system.
Moving to a quieter Chicago suburb is a completely valid option to regain your peace of mind. Street violence requires a massive combination of policing, legislative changes, economic investment, and community intervention to solve—and you are under no individual obligation to stick around and wait for that multi-decade process to play out at the expense of your own mental well-being.
###
(Put it in the spoiler, as not to pollute the thread.)I asked AI: Can these sciences cure or handle the "thugs" on the streets of Chicago who murder people every week of the year. I am concerned because I live in downtown Chicago and crime seems to be getting worse and worse. (Thinking of moving to the suburbs.)
AI: Moving to the Suburbs: Validating Your Choice
While the statistics show a downward city-wide trend, statistics do not change how you feel when walking out of your front door at night. If living downtown requires you to constantly be on high alert, scanning your surroundings, and feeling unsafe in your own home, it takes a severe toll on your nervous system.
Moving to a quieter Chicago suburb is a completely valid option to regain your peace of mind. Street violence requires a massive combination of policing, legislative changes, economic investment, and community intervention to solve—and you are under no individual obligation to stick around and wait for that multi-decade process to play out at the expense of your own mental well-being.
More on this at the end of the spoiler.
It tells me that essentially "thugs" can't be cured. Impossible or decades long task.
Not in my lifetime.
_________________________________________
Rest of the long conversation about psychiatrist/psychologist effectiveness in spoiler.
Me: Rob Reiner’s son, Nick Reiner, was admitted to drug and mental health rehabilitation facilities at least 18 times. While public reports do not state an exact total number of individual visits with psychiatrists or psychologists, investigative details outline extensive psychiatric and psychological interventions throughout his life:
Nick dealt with profound mental health challenges alongside his substance use disorder. In 2020, he was placed under a mental health conservatorship after being diagnosed with schizophrenia.
Leading up to December 2025, Nick was under the active, ongoing care of a licensed psychiatrist. During this period, he was treated at a specialized Los Angeles clinic focused on co-occurring mental health conditions and substance addictions, where doctors were actively modifying his prescription medications.
The Reiners had all the money in the world to fix the son. Nothing worked. Nobody could do anything. My question is . . . why? Do these so-called “sciences” cure anything or are they just sessions that consist of hopeful talk?
I sincerely want to know what’s going on.
It is completely understandable to feel deeply frustrated and skeptical when looking at a tragedy like this. When a family has unlimited resources, access to the top specialists, and the best available treatments, it feels like there should be a straight path to recovery. Seeing that fail leads to a very fair question: Do psychiatry and psychology actually work, or are they just expensive, hopeful talk?
The short answer is that psychiatry and clinical psychology are evidence-based sciences, but they do not offer "cures" in the traditional medical sense for severe illnesses like schizophrenia and severe substance use disorder. Instead, they treat chronic, highly complex brain disorders that—even with the best care in the world—can sometimes be treatment-resistant.
To understand why "all the money in the world" cannot guarantee a fix, it helps to look at how these sciences function, what they are fighting against, and what a "management" model looks like versus a "cure."
Schizophrenia Changes the Structure of the Brain
Schizophrenia is not an emotional problem or a behavioral choice; it is a severe neurodevelopmental and neurobiological disorder.
- Brain Alterations: Research shows that schizophrenia alters brain chemistry (particularly dopamine and glutamate pathways) and even changes physical brain structure, causing a loss of gray matter and disrupting how different regions of the brain communicate.
- Limitations of Medicine: Psychiatric medications (antipsychotics) are designed to modulate these chemicals to reduce "positive" symptoms like hallucinations and delusions. However, they do not repair the underlying structural differences in the brain. For some individuals, the brain's pathways are highly resistant to even the most advanced medications.
When a person has both a severe mental illness like schizophrenia and a substance use disorder, it is clinically referred to as a dual diagnosis or co-occurring disorder.
- The Cycle: People with untreated or under-treated schizophrenia frequently use drugs or alcohol to "self-medicate" the terrifying symptoms or the profound exhaustion of the illness.
- Chemical Interference: Illicit substances drastically alter brain chemistry, often completely neutralizing the effectiveness of psychiatric prescription medications. This creates a destructive loop: the drugs stop the antipsychotics from working, the psychosis worsens, and the worsened psychosis drives more drug use. Treating this requires simultaneously balancing complex addiction medicine with sensitive psychiatric adjustments, which is incredibly difficult to stabilize.
We often expect mental health science to behave like infectious disease medicine—where you take an antibiotic, the bacteria is killed, and you are "cured." However, psychiatry operates much more like chronic disease medicine (similar to advanced oncology, severe diabetes, or cardiovascular disease).
- No Linear Fix: Just as the wealthiest people in the world still tragically die from aggressive cancers or heart failure despite having top-tier doctors, some psychiatric conditions are fiercely aggressive.
- Therapy is Not Just Talk: Clinical psychological therapies (like Cognitive Behavioral Therapy for psychosis) are not just "hopeful conversations." They are structured interventions designed to help patients reality-test their thoughts, manage severe stress, and navigate life. But therapy requires a stabilized brain to be effective. If psychosis or active addiction is disrupting a patient's cognitive processing, therapy alone cannot break through.
If you want to understand more about how these medical fields operate, I can break down how antipsychotic medications work or explain the clinical challenges of managing a dual diagnosis. Which would you find more helpful?
Me: What can they actually cure?
While psychiatry and psychology cannot "cure" severe, structural brain disorders like schizophrenia, they can effectively cure, fully resolve, or bring into complete, lifelong remission several specific mental health conditions.
In mental health science, a "cure" is generally defined as a structured intervention that successfully eliminates the symptoms and diagnostic criteria of a disorder, allowing the individual to return to their baseline level of functioning without needing ongoing, lifelong treatment.
Here is what these sciences can actually cure or completely resolve:
1. Specific Phobias
Psychological science has an incredibly high success rate—often considered a definitive cure—for specific phobias (such as an intense, irrational fear of flying, spiders, heights, or needles).
- The Treatment: Exposure Therapy (a specific type of Cognitive Behavioral Therapy) systematically desensitizes the brain's fear center (the amygdala).
- The Outcome: Over a relatively short period (often just 6 to 12 sessions), the brain rewires itself, the phobic response is extinguished, and the person can face the trigger for the rest of their life without panic.
When mental health struggles are triggered by an external event rather than an underlying, genetic brain chemistry issue, they can be entirely cured.
- Adjustment Disorders: This is severe emotional or behavioral distress following a major life stressor (like a devastating divorce, job loss, or a move). Short-term psychotherapy provides coping mechanisms, processes the grief or stress, and completely resolves the condition once the individual adapts.
- Acute Stress Disorder & Certain Forms of PTSD: When a person experiences a traumatic event, targeted therapies like EMDR (Eye Movement Desensitization and Reprocessing) or Prolonged Exposure Therapy can successfully help the brain process and "file away" the trauma. For many individuals, this completely eliminates flashbacks and hypervigilance, effectively curing the PTSD.
Not all depression is a permanent, lifelong genetic condition. Many cases are episodic.
- Cognitive Behavioral Therapy (CBT) teaches patients to identify, challenge, and change destructive thought patterns and behaviors.
- The "Cure" Effect: Clinical trials show that for mild-to-moderate depression or generalized anxiety, a structured course of CBT can resolve the current episode entirely. Furthermore, it arms the patient with mental tools that permanently alter their cognitive habits, preventing future relapses.
Psychiatrists are medical doctors, and a massive part of their job is identifying when a "mental illness" is actually a biological glitch that can be cured instantly.
- Examples: Severe depression caused by severe hypothyroidism, or sudden psychosis caused by an autoimmune brain inflammation (like Anti-NMDA receptor encephalitis) or a vitamin B12 deficiency.
- The Cure: By accurately diagnosing the root physical cause, the psychiatrist or medical team treats the thyroid, infection, or deficiency. The psychiatric symptoms vanish completely and permanently.
To visualize how psychiatry and psychology work across different conditions, it helps to see the divide between what can be cured versus what must be managed:
Summary of the Difference
Psychiatric and psychological sciences are highly effective, but their power depends on the nature of the condition:
- The sciences CAN cure conditions born from learned fear, trauma, situational stress, or temporary cognitive distortions because the brain's physical wiring is healthy—it just needs to re-process information.
- The sciences CANNOT cure conditions born from profound neurodevelopmental differences, permanent structural changes, or severe genetic abnormalities (like schizophrenia or Bipolar I). For those, the science provides stabilization, harm reduction, and a framework to build a meaningful life with a chronic illness.
Me: Can these sciences cure or handle the "thugs" on the streets of Chicago who murder people every week of the year. I am concerned because I live in downtown Chicago and crime seems to be getting worse and worse. (Thinking of moving to the suburbs
It is completely logical that you are feeling anxious and protective of your safety. Living in downtown Chicago while constantly hearing about violent crime creates an environment of chronic stress, and considering a move to the suburbs is a very practical response to protecting your peace of mind.
To answer your question directly: Psychiatry and psychology cannot "cure" or handle street crime on their own because violent crime is not primarily a medical or psychological disease—it is a socio-economic and criminological problem.
While an individual murderer might suffer from a psychiatric disorder, a city-wide epidemic of group-based street violence is driven by systemic factors that clinical therapy sessions cannot fix. However, these sciences are used as tools within broader city strategies to suppress violence. Here is the reality of how these sciences intersect with street crime and what is actually happening with Chicago's data.
Why Medicine Can't "Cure" Street Violence
Clinical psychology and psychiatry are built to treat individuals who want help or who are placed into medical custody. They cannot handle street violence for several structural reasons:
- The Root Causes are Economic and Social: Street violence and gang culture are primarily driven by poverty, a lack of economic mobility, broken family structures, systemic educational failures, and the hyper-profitable illegal drug trade. A psychiatrist cannot prescribe a medication that fixes a neighborhood's lack of jobs or subverts the social pressure of a street gang.
- Lack of Treatment Seeking: The individuals committing weekly shootings are generally not scheduling appointments with psychologists. You cannot apply a science to a population that operates entirely outside of the medical system.
- The "Science" Used is CVI (Community Violence Intervention): Instead of traditional office therapy, criminologists and psychologists have teamed up to create Community Violence Intervention (CVI) programs. These programs employ street-level "violence interrupters"—often formerly incarcerated individuals—who use behavioral psychology to de-escalate active gang feuds and offer young people pathways out of street life. When heavily funded, CVI has proven to be highly effective at reducing shootings.
Your feeling that crime is getting worse is incredibly common, but the actual data shows a more nuanced, localized picture.
According to data compiled by the University of Chicago Crime Lab and the Chicago Police Department, Chicago actually experienced a historic, massive decline in violent crime in 2025, bucking national narratives. Homicides plummeted by roughly 29% to 30%, reaching their lowest annual levels since 1965.
As of late October 2026, the data shows that violent crime has stabilized near those historic 2025 lows:
- Homicides: Chicago Tribune data shows 341 homicides have been recorded so far in 2026, which is virtually identical to (and technically 6 fewer than) the same period in 2025.
- Other Violent Crimes: Robberies are down significantly (around 23% to 27%), and carjackings have dropped roughly 25% to 50% year-to-date.
- The Downtown Factor: While violent crime remains heavily concentrated in specific neighborhoods on the South and West Sides (like Austin and West Garfield Park), property crimes and high-profile thefts do spill into downtown areas. This visual and hyper-local reality often makes it feel like the entire city is unraveling, even when overall city-wide numbers are down.
While the statistics show a downward city-wide trend, statistics do not change how you feel when walking out of your front door at night. If living downtown requires you to constantly be on high alert, scanning your surroundings, and feeling unsafe in your own home, it takes a severe toll on your nervous system.
Moving to a quieter Chicago suburb is a completely valid option to regain your peace of mind. Street violence requires a massive combination of policing, legislative changes, economic investment, and community intervention to solve—and you are under no individual obligation to stick around and wait for that multi-decade process to play out at the expense of your own mental well-being.
###
Last edited:

HelluvaHoax!
Well-known member
"While the statistics show a downward city-wide trend,
statistics do not change how you feel when
walking out of your front door at night..."
CONCLUSION: Therefore you should seek psychiatric therapy to address your irrational feelings and fears. By referring to the color coded bar graph (above) indicating cure-rates, you can see the extraordinarily high percentile (95%) for the full resolution of SPECIFIC PHOBIAS. Thus you would be well advised to retain the professional services of a psychotherapist specializing in the heralded IFON EXPOSURE THERAPY* method.
* IFON Exposure Therapy (Gold Standard): Involves gradual, controlled, step-by-step contact with the feared object, activity, or situation to desensitize the mind and body. (IFON: Irrational Fear Of Negroes)
..
Last edited:
It's been on my to do list for a couple months to try to find out what psychologists actually DO in one of their sessions, if that's what they call them. A neighbor's daughter is studying psychology and I asked her mother if she had any books I might look at but she said it was all digital.
So I asked Google:
what reasons would one have to seek psychology therapy and what techniques might be used
Common Reasons People Seek Therapy
Common Therapeutic Techniques

National Institute of Mental Health and the
Cleveland Clinic. [1, 2]
So I asked Google:
what reasons would one have to seek psychology therapy and what techniques might be used
Common Reasons People Seek Therapy
- Mental Health Conditions: Managing symptoms of depression, anxiety, post-traumatic stress disorder (PTSD), obsessive-compulsive disorder (OCD), or eating disorders. [1, 2]
- Major Life Transitions: Coping with significant changes such as divorce, the death of a loved one, job loss, or a new career. [1, 2]
- Relationship and Conflict Issues: Resolving interpersonal struggles with a partner, family members, or coworkers, or improving communication skills. [1, 2, 3]
- Chronic Stress and Burnout: Managing overwhelming work pressure, daily life stress, or persistent sleep difficulties. [1, 2]
- Processing Trauma: Recovering from physical, emotional, or sexual abuse, or witnessing violent events. [1]
- Chronic Physical Health Issues: Adapting to the emotional and mental toll of long-term or serious medical conditions like diabetes or chronic pain. [1]
- Unhealthy Coping Mechanisms: Breaking patterns of substance misuse, impulsive reactions, or extreme emotional overwhelm. [1, 2, 3]
- General Self-Exploration: Seeking personal growth, greater self-awareness, or routine mental health maintenance. [1, 2]
Common Therapeutic Techniques
- Cognitive Behavioral Therapy (CBT): Focuses on identifying and changing unhelpful thought patterns, beliefs, and behaviors that drive emotional distress.
- Dialectical Behavior Therapy (DBT): Teaches practical skills for managing intense emotions, tolerating distress, and improving interpersonal effectiveness.
- Psychodynamic Therapy: Explores unconscious thoughts, past experiences, and childhood roots that influence current behavior.
- Interpersonal Therapy (IPT): A short-term approach aimed at resolving relationship conflicts and improving social functioning.
- Exposure Therapy: Helps individuals gradually and safely confront fears, phobias, or trauma-related triggers to reduce avoidance and anxiety.
- Mindfulness and Coping Strategies: Integrates present-moment awareness, relaxation, and self-regulation techniques to handle stress.
- Humanistic / Client-Centered Therapy: Empathy-driven therapy that emphasizes personal growth, self-acceptance, and rational choice. [1, 2, 3, 4, 5]
National Institute of Mental Health and the
Cleveland Clinic. [1, 2]

cbtcenter.org
Top 10 Reasons People Seek Therapy | CBT Center NJ


Cleveland Clinic
Psychotherapy: What It Is, Why It Is Done & Types

American Psychological Association (APA)
Different approaches to psychotherapy

Last edited:
^ ^ ^ ^ ^ ^ ^
Now that I'm down the rabbit hole this came up. I also looked at the spoiler @ILove2Lurk posted and it has information. Maybe I'll get some credits for being a certified Scn auditor if I decide to go back to grad school and study psychology? Most auditors already dealt with most of the "Common Reasons People Seek Therapy" listed by Google.
Date created: December 11, 2019
3 min read
Now that I'm down the rabbit hole this came up. I also looked at the spoiler @ILove2Lurk posted and it has information. Maybe I'll get some credits for being a certified Scn auditor if I decide to go back to grad school and study psychology? Most auditors already dealt with most of the "Common Reasons People Seek Therapy" listed by Google.
What do practicing psychologists do?
Practicing psychologists have the professional training and clinical skills to help people learn to cope more effectively with life issues and mental health problems.Date created: December 11, 2019
3 min read
Last edited:
Laughter! Wogs hearing Scientologists using the term "meat bodies" might wonder what in the world are these people talking about!Doctors have to allow that you're more than flesh before clients can step a bit to the side and view that head they've been wearing. Too many wrongly assigned causes, might be worse than not stating any.

ILove2Lurk
. . Lisbeth Salander . . Back in Sweden
~
"While the statistics show a downward city-wide trend,
statistics do not change how you feel when
walking out of your front door at night..."

"No they don't."
"While the statistics show a downward city-wide trend,
statistics do not change how you feel when
walking out of your front door at night..."
"No they don't."
Hatshepsut
Well-known member
I'm surprised AI even conceded there was ever a city-wide problem. It used to correct your attitude and window for viewing the subject, before giving specific data.

Enthetan
Veteran of the Psychic Wars
Psychs are a good way to implement mind control. LRH just didn’t want any competition from HIS particular brand of mind control.It's an odd day when I find myself agreeing with L Ron Hubbard on something. This is coincidental. I highly doubt he would have seen this one coming though. Accidental prophet...

Type4_PTS
Well-known member
Can anyone explain why I shouldn't just believe these practices to be "fake practices?"
I don't like to characterize them as "fake practices" because they do help some people with certain issues. But I am not a fan of the psychiatric profession. There is a LOT of fraud. They've been captured by Big Pharma, and the government agencies that are supposed to be regulating them have also been captured. Here is an interesting blog post from Substack. It includes information about STAR*D, which was the largest depression trial ever conducted. The National Institute of Mental Health funded it. It was designed by the profession’s most senior researchers. What it proved, when honestly analyzed, was that the drugs did not work.
12 Things Your Psychiatrist Was Trained Not to Tell You
An Essay on What the Fifteen-Minute Consultation Leaves Out
Unbekoming
Sep 10, 2026

12 Things Your Psychiatrist Was Trained Not to Tell You
An Essay on What the Fifteen-Minute Consultation Leaves Out
 www.unbekoming.com
What follows is twelve documented findings compressed into one sitting. It is written for the reader who has been prescribed one of these drugs, or is caring for someone who has, and who wants to know what the fifteen-minute consultation did not include. Every claim is drawn from the profession’s own literature, its own regulatory filings, its own package inserts, or the admissions of its own senior figures. Where an item is developed at greater length elsewhere in this series, that is noted. The purpose here is not depth on any single item. It is the cumulative weight of the twelve landing together.
Opening
Three percent of the 4,041 patients enrolled in the STAR*D trial remitted, stayed well, and remained in the study through the one-year follow-up.¹The trial was announced with a cumulative remission figure of 67 percent.² When Ed Pigott and colleagues spent more than five years reanalyzing the data with fidelity to the original protocol, they found the 3 percent figure. When journalists put the 3 percent number to Maurizio Fava, one of the lead investigators, he acknowledged it was accurate. The investigators knew.³
The paper has not been retracted. It is still cited in psychiatric textbooks. The American Journal of Psychiatry ignored a petition signed by more than 1,800 people asking for retraction. The New York Times, repeatedly notified of the fraud, published the 70 percent figure again in a 2024 article praising the drugs.⁴
STAR*D was the largest depression trial ever conducted. It was funded by the National Institute of Mental Health. It was designed by the profession’s most senior researchers. What it proved, when honestly analyzed, was that the drugs did not work.
That fact has been available for over a decade. It has not reached the patients being handed the prescriptions.
What This Essay Draws On
Six of the twelve items below have been developed at greater length in earlier essays in this series: chemical imbalance theory, benzodiazepine dependence, ADHD stimulants, antipsychotic brain damage, SSRI withdrawal, and long-term antidepressant outcomes. Readers who want depth on any of those threads should follow them. The purpose of this essay is different. Twelve items, four sections, one sitting.The evidence throughout is drawn primarily from Peter Gøtzsche, Robert Whitaker, Peter Breggin, Gary Greenberg, David Healy, and Joanna Moncrieff. What the twelve items share is that none of them are contested at the level of documentation. They are contested only at the level of what the profession chooses to tell patients.
What They Told You Was True
The prescription is written on the basis of a mechanism, a diagnosis, and a trial. Each has failed on its own terms.1. The chemical imbalance was never demonstrated
The theory that depression results from a deficiency of serotonin was never established in the scientific literature. Joanna Moncrieff and colleagues published a comprehensive umbrella review of the serotonin theory in 2022 and found no consistent evidence for its central claims.⁵ The theory was abandoned by serious researchers decades earlier. It continued to appear in direct-to-consumer advertising and patient education materials because it served a function. It explained why the pill was necessary and why the patient would need to keep taking it.Steven Hyman, director of NIMH from 1996 to 2001, later observed that “the gold standard was the DSM criteria. It struck me as a fool’s errand to try to develop a biomarker for a fictive category.”⁶ The chemical imbalance was the mechanism proposed for a disease no one could measure, in a category no one could validate.

Chemical Imbalance: The Collapse of a Medical Myth
Unbekoming·
December 22, 2025
Read full story
2. The DSM has no biological markers
After four decades and hundreds of millions of dollars in federal research, not one disorder in the Diagnostic and Statistical Manual of Mental Disorders has a confirmed biological test. Not depression. Not schizophrenia. Not bipolar disorder. Not ADHD. Not anxiety. Not any of the more than three hundred conditions the manual lists.Robins and Guze proposed a five-step validation process in 1970: clinical description, laboratory studies, exclusion criteria, follow-up studies, family studies.⁷ The five steps were meant to establish, over time, which alleged disorders were real diseases and which were figments. Four decades later, Darrel Regier, who chaired the DSM-5 task force, told Psychiatric News that “validity tests have not lived up to the expectations of Robins and Guze.”⁸ Kenneth Kendler, the field’s leading nosologist, wrote that the diagnostic categories in use had been “heavily influenced by expert opinion” and were “fuzzy constructs that shift when viewed in different ways.”⁹
Thomas Insel, director of NIMH from 2002 to 2015, put it most directly in a 2005 address to the American Psychiatric Association: “The DSM-IV has 100 percent reliability and zero percent validity.”¹⁰ Reliability means clinicians using the same manual will arrive at the same diagnosis. Validity means the diagnosis corresponds to a real thing. Insel was telling the assembled profession that its manual sorted patients consistently into categories that did not exist.
The APA response was to convene committees to plan the DSM-5. The committees did not find biological markers. They could not have. The categories were not built to have biological markers. They were built from clinical description alone. The manual reifies its own criteria.
The consequence for the patient is direct. When the doctor says “you have major depressive disorder,” the patient hears a diagnosis in the sense that a diabetes diagnosis is a diagnosis: a measurable biological state with a known mechanism. What the patient has actually received is a checklist tally. Five of nine symptoms present for two weeks. That is the whole test. There is no blood work, no scan, no biomarker. The diagnostic bible of American psychiatry sits on the shelf as an artifact of expert agreement, not a description of nature.

Manufacturing Madness: The DSM as Instrument of Social Control
Unbekoming·
October 15, 2025
Read full story
3. STAR*D was manipulated
The opening figures bear structural repetition: 3 percent versus 67 percent, admitted by the lead investigator, still not retracted, still cited. Ed Pigott’s reanalysis was published in BMJ Open in 2023.¹¹ The investigators, when confronted, doubled down on the fraud in the American Journal of Psychiatry rather than correct it.¹² The owner of the journal, the American Psychiatric Association, did nothing.Peter Gøtzsche has documented the specific manipulations. The “remission” threshold was set so low that a patient scoring 7 on the Hamilton depression scale, including endorsement of “feels like life is not worth living,” was counted as symptom-free.¹³ Patients who exited the study were assumed to have remitted at the same rate as those who stayed, a statistical fiction that inflated the numbers by an order of magnitude. Eleven prespecified outcomes were never reported. Suicidal ideation was reported at 0.7 percent in one paper and ten times that in others by the same authors.
The trial that was supposed to establish the effectiveness of antidepressants in real-world practice established the opposite. The profession’s response was to continue citing the announced figure.

Is Psychiatry a Crime Against Humanity? (2024)
Unbekoming·
January 1, 2025
Read full story
What Happens on the Drug
The prescription arrives with the phrase “you may notice some side effects.” The phrase does the work of concealment. Three effects, in particular, are not warned about with the seriousness they warrant.4. Akathisia carries documented suicide risk
Akathisia is a state of extreme inner restlessness produced by antidepressants, antipsychotics, and antiemetics. The Greek term means inability to sit still. The patient may pace, fidget, wring hands, or endlessly walk. The condition may also present without visible motor symptoms, as unbearable internal agitation the observer cannot see.¹⁴In 1990, Martin Teicher and colleagues at Harvard published five cases of patients who developed intense suicidal preoccupations on fluoxetine, all associated with akathisia, all resolving when the drug was stopped and returning when it was restarted.¹⁵ Rothschild and Locke published the rechallenge study in 1991: three patients who had made serious suicide attempts on fluoxetine, all rechallenged under controlled conditions, all developing akathisia and becoming suicidal again. One patient said in retrospect: “I tried to kill myself because of these anxiety symptoms. It was not so much the depression.”¹⁶
A study of psychiatric inpatients found that 79 percent of those who had attempted suicide were experiencing akathisia at the time.¹⁷ Another found that half of all fights on a psychiatric ward were akathisia-related. Haloperidol at moderate to high doses made half the patients markedly more aggressive, sometimes to the point of wanting to kill their psychiatrists.
The FDA’s 2004 black-box warning on antidepressants describes what Breggin has called the stimulant syndrome: anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia, hypomania, mania.¹⁸ The label warns that these can occur in nonpsychiatric patients, meaning the drug produces the syndrome by itself, not by unmasking a preexisting condition.
Gøtzsche’s team examined manufacturer trial data and found akathisia miscoded as “hyperkinesia” in Zoloft trials. In paroxetine trials they found not a single case of akathisia recorded, which is statistically impossible given the drug class.¹⁹ The miscoding was systematic.
The FDA-approved label for Zyprexa describes akathisia as “extreme inner anxiety and restlessness.” At least one psychiatric textbook labeled it “agitated depression,” folding the drug’s most dangerous effect back into the diagnosis it was prescribed to treat. The patient who reports the akathisia is told the underlying illness has worsened. The dose is increased.

Mental Health Survival Kit and Withdrawal from Psychiatric Drugs (2022)
Unbekoming·
Jun 1
Read full story
5. Benzodiazepine dependence begins at prescribed doses
The FDA-approved label for Xanax states that withdrawal symptoms, including seizures, have been reported after only brief therapy at doses within the recommended range for treating anxiety.²⁰ In the eight-week trials used for FDA approval, patients were worse off at eight weeks than before starting the drug. Between 7 and 29 percent of patients could not withdraw after only six to eight weeks of exposure.²¹If you are currently taking a benzodiazepine, do not stop it abruptly. Abrupt cessation can produce seizures. Item 12 addresses what safe withdrawal actually requires.
Heather Ashton, the British psychiatrist who ran a benzodiazepine withdrawal clinic at the University of Newcastle for decades, documented that long-term users often required a year or more to taper.²² Some experience withdrawal symptoms lasting years after cessation. Cognitive impairment, depression, and anxiety worse than the original condition are common outcomes of long-term use.²³ Gøtzsche, who has decades of clinical pharmacology experience, has noted that patients report benzodiazepine withdrawal as often worse than heroin. Heroin abstinence symptoms resolve within days. Benzo withdrawal can persist for years.

Anxiety Uncovered: The Truth About Benzodiazepines and Real Solutions
Unbekoming·
May 2, 2025
Read full story
6. ADHD stimulants produce the symptoms they treat on withdrawal
The DSM has a category for stimulant withdrawal, which lists depression, anxiety, irritability, sleep problems, fatigue, and agitation as the withdrawal syndrome after “several days or longer” of use. Rebound hyperactivity, talkativeness, and inattention are documented after a single dose in a placebo-controlled NIMH study of normal children ages 6 to 12.²⁴ Ten of fourteen children in that study showed marked behavioral rebound; three developed euphoria.If a child is currently taking a stimulant, do not stop it abruptly. Rebound and withdrawal effects are commonly mistaken for a worsening of the original condition. Item 12 addresses safe withdrawal.
The teacher observes the child on Monday morning after a weekend off the drug, notices the child is more scattered and irritable than usual, and concludes the child needs the medication. The child is in withdrawal. The dose is increased. Peter Breggin’s observation from the early 1990s stands unchanged three decades later: if the child continues on Ritalin because they continue to have problems focusing, the disorder may be the drug’s effect.²⁵ Drug-induced inattention becomes the reason to continue and increase the drug.
The Multimodal Treatment Study of ADHD, the largest NIMH-funded stimulant trial, tracked children through eight years of follow-up. By three years, the medicated children showed no advantage over the non-medicated on any measure. They were, however, 2 cm shorter and 2.7 kg lighter than their unmedicated peers, a growth suppression the FDA eventually required on the label.²⁶

The Arithmetic Pill: ADHD, ADD, and the Evidence
Unbekoming·
December 25, 2025
Read full story
What Happens to Your Brain
The drugs act on the brain and the brain responds. What the brain does under sustained chemical assault is documented in the profession’s own imaging studies.7. Antipsychotics shrink brain tissue on MRI
Nancy Andreasen, editor-in-chief of the American Journal of Psychiatry from 1993 to 2005, began a longitudinal MRI study of over 500 first-episode schizophrenia patients in 1989. In 2003, she reported that frontal lobe white matter volume decreased progressively over the years of treatment.²⁷ In 2011, her team published in Archives of General Psychiatry the finding that antipsychotic exposure was directly associated with volume loss.²⁸ In a 2008 interview with the New York Times, Andreasen stated it plainly: “The more drugs you’ve been given, the more brain tissue you lose.”²⁹Fusar-Poli and colleagues confirmed the pattern in a 2013 meta-analysis of longitudinal MRI studies.³⁰ The 2009 Navari and Dazzan review reported that both older and newer antipsychotics produce gross changes in brain volume in selected regions.³¹ In monkey studies, haloperidol and olanzapine produced substantial reductions in both grey and white matter, and reduced glial cell numbers.³²
Andreasen’s original interpretation was that the shrinkage reflected the disease. The follow-up data forced her to concede the drug was the cause.

Anatomy of an Epidemic: Magic Bullets, Psychiatric Drugs, and the Astonishing Rise of Mental Illness in America (2010)
Unbekoming·
May 21
Read full story
8. Tardive dyskinesia is permanent
Tardive dyskinesia is a drug-induced movement disorder produced by antipsychotics. It can affect any voluntary muscle: face, tongue, neck, torso, extremities, diaphragm, vocal cords. The condition presents as involuntary jerky movements, slower writhing movements, painful spasms, or restlessness the patient cannot control. The mechanism is understood. Antipsychotics block dopamine receptors in a brain region called the basal ganglia. Over time the brain compensates by growing more of those receptors. When the drug dose is reduced, or when the extra receptors eventually outnumber the block, the excess drives the involuntary movements.The prevalence is not marginal. DSM-IV-TR sets the annual incidence at 3 to 5 percent per year in young adults and 25 to 30 percent per year in older patients.³³ These are cumulative rates. A young adult after three years of exposure has a 9 to 15 percent risk. An older patient after three years has a 75 to 90 percent risk. Prevalence in outpatient clinics runs above 40 percent. In long-term facilities, above 50 percent.³⁴ There is no established treatment. Most cases are permanent.
The condition often extends beyond motor symptoms. Gualtieri and Barnhill observed that “in virtually every clinical survey that has addressed the question, it is found that TD patients, compared to non-TD patients, have more in the way of dementia.”³⁵ Breggin has called this tardive dementia. Tardive akathisia and tardive psychosis have also been documented, representing further permanent damage to the higher brain function of patients whose brains were supposed to be helped.
The condition is frequently masked by the drug that caused it. Increasing the dose suppresses the visible movements while the underlying damage progresses. Reducing the dose brings the movements out, which the prescriber may interpret as evidence that the patient still needs the medication. The patient’s brain, already damaged, is offered more of what damaged it.
The neurological literature has documented tardive dyskinesia for over five decades. It is required disclosure on antipsychotic labels. It is not routinely disclosed at the point of prescription.

Toxic Psychiatry
Unbekoming·
December 17, 2024
Read full story
9. ECT causes documented brain damage
Electroconvulsive therapy applies electrical current to the head sufficient to produce a grand mal seizure. In modern practice, the patient is anesthetized and given a muscle relaxant to prevent the visible convulsion. The electrical dose is often increased to compensate for the seizure threshold raised by the anesthesia. Multiple treatments are given, typically 8 to 16 per course, sometimes more.Autopsy studies dating to the 1940s documented brain necrosis in patients who died following ECT.³⁶ Animal studies documented brain damage. The brain’s response to ECT is an acute organic brain syndrome, medically indistinguishable from severe head injury. In neurological terms, multiple continuous seizures without full recovery of consciousness constitute status epilepticus, a medical emergency defined by its risk of permanent brain damage.
The memory loss is documented in every serious study that has looked for it. Larry Squire and Pamela Slater reported an average of 27 months of retrograde amnesia surrounding treatment.³⁷ Freeman and Kendell, using face-to-face interviews conducted by the treating doctors themselves (a design that biased strongly against reporting), found that 74 percent of patients reported memory impairment and 30 percent said their memory function was permanently affected.³⁸ Squire and Slater’s own longer follow-up found that 55 percent of patients felt they had not regained normal memory function over the years.
Gøtzsche summarizes the current literature: with strict definitions of memory loss, 29 to 55 percent of patients are affected. With looser criteria, 51 to 79 percent.³⁹ Death rates from ECT, according to a systematic review by John Read and colleagues, run at approximately 1 per 1,000 treatment courses, ten times higher than the American Psychiatric Association’s stated figure.⁴⁰
The efficacy evidence is thinner than the harms evidence. The 1985 NIMH Consensus Conference on ECT accepted the finding that no controlled study showed benefit beyond four weeks. The four-week window corresponds to the acute organic brain syndrome, during which severe brain dysfunction produces the euphoria or apathy interpreted as improvement.⁴¹ Once the brain begins to recover, the depression returns. If the patient is given more ECT, the brain damage accumulates. If the patient is not given more ECT, the profession points to the returning depression as evidence the disease was chronic.
The APA’s 1990 task force report on ECT omitted essentially the entire literature documenting memory loss and brain damage.⁴² The literature it omitted included the work of Squire, Slater, Janis, Friedberg, Breggin, and even the APA’s own previous 1978 report, which contained more information on memory loss than the 1990 update. In psychiatry, science sometimes runs backward.

The Top 10 Myths of Modern Psychiatry
Unbekoming·
December 23, 2025
Read full story
What Happens When You Try to Leave
At some point the patient decides they no longer want to be on the drug. The system was not built to help them leave.10. SSRI discontinuation can last years
The FDA-approved labels describe “discontinuation syndrome.” Patients and doctors alike were told the symptoms would last a few weeks and resolve. The systematic review by Davies and Read, published in 2019, established that this was false. Withdrawal symptoms are more common than reported, more severe than reported, and last far longer than reported. In one survey of 580 patients, 16 percent reported withdrawal symptoms lasting over three years.⁴³If you are currently taking an SSRI or SNRI, do not stop it abruptly. Withdrawal reactions can include severe agitation, akathisia, suicidal ideation, and violence. Item 12 addresses the resources for safe tapering.
The Dutch tapering-strip program run by Peter Groot and Jim van Os has documented the shape of the problem. Of 895 patients on antidepressants, 62 percent had previously tried to withdraw without success. Using hyperbolic dose-reduction strips, 71 percent were able to withdraw within a median of 56 days.⁴⁴ Venlafaxine required 90 percent of patients to start at the lowest available dose and taper over three months. Some patients required more than six months. Dutch insurers refused to reimburse extended tapering because “there is no evidence in the literature” for its necessity, a circular defense against the very treatment the literature was documenting.
The withdrawal is routinely misinterpreted as return of the underlying illness. The patient is told they were unwise to stop and needs to remain on the drug indefinitely. Breggin’s term for this pattern is medication spellbinding. The drug produces effects the patient attributes to the disease.

What to Ask Before Your Next Antidepressant Prescription
Unbekoming·
Jun 13
Read full story
11. Long-term outcomes are worse with the drugs than without them
The 1997 British study of a large inner-city primary care facility followed 95 never-medicated depressed patients and 53 drug-treated ones. Symptom reduction at six months: 62 percent for the never-medicated, 33 percent for the drug-treated.⁴⁵ A World Health Organization study of 640 depressed patients found that medicated patients had worse general health and were more likely to still be mentally ill at one year.⁴⁶ A Canadian five-year study of 9,508 depressed patients: 19 weeks of depression per year for the medicated, 11 for the unmedicated.⁴⁷ An NIMH study of 547 patients: medicated patients were three times more likely to lose their principal social role and nearly seven times more likely to become incapacitated at six years.⁴⁸Rif El-Mallakh reported that 40 percent of patients on antidepressants end up in a chronically depressed “treatment resistant” state.⁴⁹ Giovanni Fava documented that drug changes induced by antidepressants “may propel the illness to a more malignant and treatment unresponsive course.”⁵⁰
The pattern extends to antipsychotics. Martin Harrow’s 15-year follow-up of first-episode psychosis patients found that those not on antipsychotics had significantly better outcomes and were far more likely to be in recovery.⁵¹ Lex Wunderink’s 7-year Dutch trial randomized first-episode psychosis patients to maintenance antipsychotics or dose reduction and discontinuation. The reduction group had double the recovery rate.⁵² Bockoven had documented in 1975 that rehospitalization rates rose after the introduction of antipsychotics and that medicated patients were more socially dependent than those treated in the pre-drug era.⁵³
The pattern is consistent across drug classes and across decades. Longer exposure produces worse outcomes. The drugs sensitize the brain and convert episodic distress into chronic dysfunction. The profession’s response has been to rewrite the natural history of the conditions to match the drug-damaged outcomes. The 1999 American Psychiatric Publishing Textbook of Psychiatry declared that older studies showing depression was self-limiting had been “disproved.” Depression became “a highly recurrent and pernicious disorder.”⁵⁴ The drugs had made it so.
Feeling Better, Getting Worse: How Psychiatric Drugs Create the Illusion They Cure
Feeling Better, Getting Worse: How Psychiatric Drugs Create the Illusion They Cure
Unbekoming·
Apr 9
Read full story
12. Tapering protocols do not exist in most medical schools
The prescriber who put the patient on the drug is typically not trained in how to help them come off it. Withdrawal is not covered in the standard psychiatric curriculum. The tapering approach with the strongest evidence base is hyperbolic dose reduction, developed by Mark Horowitz and Joanna Moncrieff and published in Lancet Psychiatry in 2019.⁵⁵ The approach requires micro-dose reductions of a few percent at a time, made possible by liquid formulations or compounded tapering strips. Standard tablets do not come in the small doses required.Peter Gøtzsche’s team spent two years trying to publish a Cochrane review protocol on antidepressant withdrawal support. The Cochrane depression group, chaired by Rachel Churchill, raised objections through 12,044 words of feedback across 86 numbered points, then rejected the protocol.⁵⁶ Cochrane refused to publish a review on how to help patients safely withdraw from a class of drugs prescribed to hundreds of millions of people worldwide. Gøtzsche’s PhD student Anders Sørensen mentored 30 consecutive patients through withdrawal in his unpaid spare time and documented the results, because it was the only way to do the work.
The insurance system compounds the problem. Dutch national health insurance refuses to reimburse extended tapering on the grounds of insufficient evidence, though the evidence exists and the insurers know it does. American insurers do not cover compounded formulations. The tapering strips developed at the Amsterdam pharmacy (taperingstrip.org) are available to prescribers in any country, but the patient must find a prescriber willing to order them, which many will not.
The knowledge exists. The Ashton Manual for benzodiazepine withdrawal has been public since 2002.⁵⁷ The Horowitz-Moncrieff hyperbolic tapering literature is in peer-reviewed journals. Mad in America hosts a withdrawal community with thousands of patients’ documented experiences. Breggin’s Psychiatric Drug Withdrawal was published in 2013.
None of it is on the psychiatric residency reading list. The doctor who wrote the prescription is, in most cases, not the doctor who can help the patient stop taking it. The patient is on their own.
Escape from Psychiatry
Escape from Psychiatry
Unbekoming·
Apr 10
Read full story
What This Does Not Mean
The most common defense of the current prescribing paradigm is that the drugs help some patients, and that essays like this one endanger those patients by encouraging them to stop.Some patients do report subjective benefit on these drugs. That is not disputed. What is not established is that this benefit exceeds placebo by a clinically meaningful margin, or that it survives the long-term outcomes documented in Item 11.
The safety caveats throughout this essay, and the resources listed below, exist precisely because abrupt cessation is dangerous. Nothing here recommends abrupt cessation. What is recommended is informed choice, which requires the twelve findings to be visible before the prescription is written or renewed. A patient who wishes to continue after seeing the twelve findings has made a different decision from a patient who was never shown them.
<snip> Full Post (including 58 references) at the link above.
ILove2Lurk
. . Lisbeth Salander . . Back in Sweden
Thank you!Here is an interesting blog post from Substack.

Stuff I had no clue about. (Great substack!!! These are REALLY good articles!)
CONCLUSION: Therefore you should seek psychiatric therapy to address your irrational feelings and fears. By referring to the color coded bar graph (above) indicating cure-rates, you can see the extraordinarily high percentile (95%) for the full resolution of SPECIFIC PHOBIAS. Thus you would be well advised to retain the professional services of a psychotherapist . . . .
This graph above (from my initial AI research attempt) explains a lot for me.
The most severe problems are hardly understood or have know treatments. Lighter issues in life
-- like a neighbor smoking pot and it wafting over into my yard and I'm mildly upset -- possibly
resolved with enough therapy or group therapy.
So here, as my mea culpa, is my list of current character flaws/psychological flaws/phobias I would like to have cured.
- Not liking people calling me a racist or homophobe
- Not liking people calling me out derogatorily as "Trump person"
- Not liking people referring to me derogatorily as white or white privileged
- Not liking neighbor smoking pot outside occasionally and it wafting over into my yard or open windows
- Not liking most of the news articles I read on the Internet nowadays; rather depressing
- Not liking to have to be concerned about computer security so much nowadays
- Not liking most Hollywood movies or shows on TV nowadays
- Fear of a car full of Sea Org pulling into the driveway (I actually resolved this ten years ago)
- Fear of civilians finding out I was a scientologist for so long in my distant past
- Afraid of walking in "dark people" neighbor(hoods) or "no-go zones"
- Afraid of driving in or near "dark people" neighbor(hoods) or "no-go zones"
- Afraid of flying anymore (too many fights, potential problems and long lines)
- Afraid of the streets and sidewalks of San Francisco (15 years since last visit there)
- Busy or packed highways (I only drive in off-peak hours)
Any hope for me? ¯\_(ツ)_/¯
Last edited:

